
Hip Bursitis MRI and Ultrasound Signs: Trochanteric Bursa
Hip bursitis, most commonly trochanteric bursitis, is part of the greater trochanteric pain syndrome (GTPS) spectrum that includes inflammation of the trochanteric bursa and pathology of the gluteal tendons. The trochanteric bursa lies between the greater trochanter of the femur and the iliotibial band, and when inflamed it produces lateral hip pain that can significantly limit daily activities. Modern imaging has revealed that isolated bursitis is less common than previously thought, with gluteal tendinopathy or tears being the primary pathology in most cases.
Common Symptoms
- Point tenderness directly over the greater trochanter, reproducible with direct pressure
- Lateral hip pain that radiates down the outer thigh and worsens when lying on the affected side
- Pain with climbing stairs, rising from a chair, or walking on uneven surfaces
- Snapping sensation along the lateral hip associated with movement of the iliotibial band over the trochanter
- Increased pain with prolonged standing or sitting with legs crossed
- Night pain that disrupts sleep, particularly in patients who prefer side-lying positions
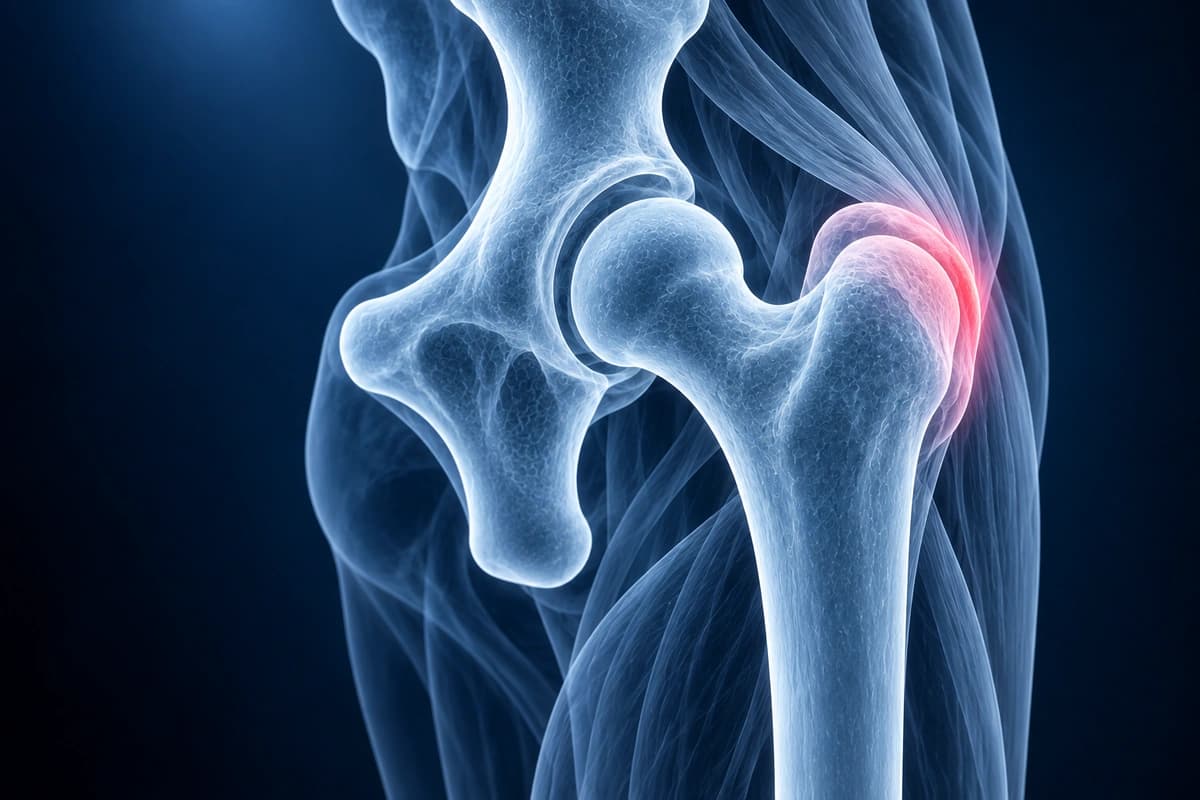
For search and clinical clarity, hip bursitis should be framed as greater trochanteric pain syndrome rather than a single fluid pocket. MRI separates isolated bursal fluid from gluteal tendinopathy, partial tendon tears, iliotibial band friction, and referred intra-articular pain such as hip labral tear. For cam and pincer mechanics, read the FAI cam vs pincer MRI guide.
Hip X-rays can help exclude arthritis, calcific tendinopathy, fracture, or prominent greater trochanteric spurs, but they do not show bursal inflammation directly. CT is mainly useful when bone detail is the question. For soft-tissue review, use MRI or ultrasound, then compare related findings in the free hip MRI viewer or free hip X-ray viewer. Use the free hip CT viewer when fracture, calcification, or hardware detail is the focus.
What We Look For on Imaging
- Fluid distension of the trochanteric or subgluteus maximus bursa
- Gluteus medius or minimus tendinopathy with signal abnormality and thickening
- Partial or complete gluteal tendon tear at the greater trochanter insertion
- Peritrochanteric soft tissue edema on fluid-sensitive sequences
- Bone marrow edema at the greater trochanter attachment sites
- Iliotibial band thickening or friction-related signal changes
Frequently Asked Questions
What distinguishes trochanteric bursitis from gluteal tendinopathy on imaging?
The two conditions frequently coexist but are anatomically distinct. Trochanteric bursitis refers to inflammation of one or more bursae between the greater trochanter and the overlying iliotibial band or gluteal tendons. Gluteal tendinopathy involves intrinsic tendon degeneration of the gluteus medius or minimus at their trochanteric insertions. On MRI, bursitis appears as T2 hyperintense fluid signal in the subgluteal space lateral and posterior to the trochanter. Tendinopathy manifests as intrasubstance T2 signal within the tendon footprint, with or without partial-thickness tearing, detectable on coronal fat-suppressed sequences. Distinguishing the two is clinically important because isolated bursitis responds well to corticosteroid injection, while gluteal tendinopathy is best managed with load-management physiotherapy and may require tendon repair or augmentation if a full-thickness tear is present.
What role does ultrasound play in diagnosing and treating hip bursitis?
A randomized trial found no better outcomes with fluoroscopy-guided corticosteroid injection than with landmark-guided injection for greater trochanteric pain syndrome.
Can MRI show hip bursitis?
MRI can show trochanteric or subgluteal bursal fluid, peritrochanteric edema, gluteal tendon disease, and marrow reaction near the greater trochanter. These findings support the imaging impression, but a clinician still needs to match them with the pain location, examination, and other possible causes of lateral hip pain.
Can X-ray or CT diagnose hip bursitis?
X-ray and CT can support the workup by showing hip osteoarthritis, fracture, enthesophytes, calcific deposits, or hardware-related causes of lateral hip pain, but they usually cannot confirm bursitis itself. MRI and ultrasound are better for seeing trochanteric bursal fluid, gluteus medius or minimus tendon disease, and peritrochanteric edema.
When is CT better than MRI for lateral hip pain?
CT is better when the main question is cortical fracture, hardware position, post-operative bone detail, or mineralized calcification around the greater trochanter. MRI is usually better for bursitis, gluteal tendons, marrow edema, and other soft-tissue causes. CT findings should not be used alone to confirm or exclude symptomatic bursitis.
What should a clinician confirm before calling it hip bursitis?
A clinician should confirm that the pain is lateral and reproducible over the greater trochanter, check hip abductor strength and gait, review gluteus medius and minimus tendons, and consider referred lumbar, intra-articular hip, inflammatory, infectious, or post-surgical causes when the story does not fit simple greater trochanteric pain syndrome.
What can AI not diagnose about hip bursitis?
Outer hip pain may arise from gluteal tendons as well as bursae, and imaging findings need clinical correlation. AI cannot establish which structure is causing pain.
Are there specific risk factors that predispose patients to recurrent trochanteric bursitis?
A community-based study found no association between leg-length inequality and greater trochanteric pain syndrome.
Sources
- Kingzett-Taylor A, Tirman PF, Feller J, et al. Tendinosis and tears of gluteus medius and minimus muscles as a cause of hip pain: MR imaging findings. AJR Am J Roentgenol. 1999;173(4):1123-1126.
- Long SS, Surrey DE, Nazarian LN. Sonography of greater trochanteric pain syndrome and the rarity of primary bursitis. AJR Am J Roentgenol. 2013;201(5):1083-1086.
- Cohen SP, Strassels SA, Foster L, et al. Comparison of fluoroscopically guided and blind corticosteroid injections for greater trochanteric pain syndrome: multicentre randomised controlled trial. BMJ. 2009;338:b1088.
- Segal NA, Harvey W, Felson DT, et al. Leg-length inequality is not associated with greater trochanteric pain syndrome. Arthritis Res Ther. 2008;10(3):R62.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer