
Piriformis Syndrome on MRI & X-ray: Imaging Findings
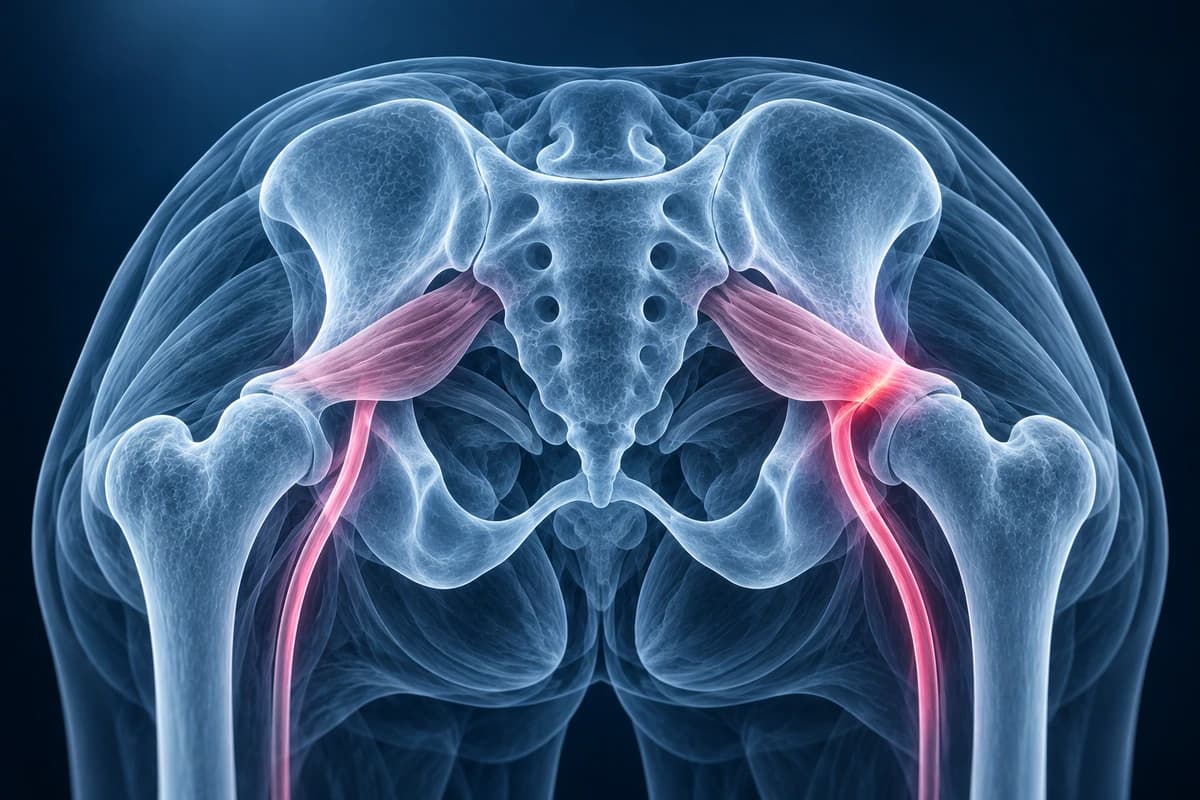
Piriformis syndrome is a neuromuscular condition in which the piriformis muscle, located deep in the buttock, compresses or irritates the sciatic nerve. This produces deep buttock pain that often radiates down the posterior thigh, mimicking lumbar radiculopathy. The piriformis muscle originates from the anterior sacrum and inserts on the greater trochanter, with the sciatic nerve typically passing beneath or, in anatomical variants, through the muscle belly. Diagnosis can be challenging because symptoms overlap with lumbar disc herniation, and imaging plays an important role in excluding spinal pathology and identifying piriformis muscle abnormalities. AI can help explain report terms about the piriformis and sciatic nerve, but it cannot confirm piriformis syndrome or identify the cause of your pain.
Common Symptoms
- Deep buttock pain localized to the piriformis region, often described as a dull persistent ache with episodic sharp exacerbations
- Sciatic nerve irritation producing posterolateral leg pain, paresthesia, or numbness radiating below the knee, mimicking lumbar disc herniation
- Pain worsening with prolonged sitting on hard surfaces, particularly when the hip is flexed and internally rotated
- Tenderness on deep palpation of the piriformis muscle medial to the greater trochanter or at its sciatic notch insertion
- Pain reproduced by the FAIR test — hip Flexion, ADduction, and Internal Rotation — which stretches the piriformis against the sciatic nerve
- Aggravation during activities placing the hip in a figure-four position, such as cross-legged sitting or driving with the hip externally rotated
What We Look For on Imaging
- Piriformis muscle asymmetry with enlargement or hypertrophy on the affected side
- Increased T2 signal within the piriformis indicating muscle edema or inflammation
- Sciatic nerve signal abnormality or asymmetric enlargement at the sciatic notch
- Anatomical variant with the sciatic nerve passing through the piriformis muscle
- Atrophy or fatty infiltration of the piriformis in chronic cases
- Exclusion of lumbar disc pathology or sacroiliac joint abnormalities as alternative causes
Frequently Asked Questions
How is piriformis syndrome diagnosed when lumbar pathology must be excluded?
Piriformis syndrome is a clinical diagnosis of exclusion, requiring that lumbar spine pathology be ruled out as the source of sciatic nerve irritation. MRI of the lumbar spine excludes disc herniation, foraminal stenosis, and intrapelvic mass compressing the sacral plexus. If lumbar MRI is normal, MRI of the pelvis with dedicated coronal and axial sequences through the greater sciatic notch can identify piriformis muscle hypertrophy, asymmetry, anomalous fiber bundles splitting around the sciatic nerve, myositis, hematoma, or a bifid piriformis — structural variants that predispose to nerve entrapment. Electrodiagnostic studies (EMG and nerve conduction velocity) can corroborate sciatic nerve dysfunction at the piriformis level, although normal studies do not exclude the diagnosis. Diagnostic injection of local anesthetic and corticosteroid into the piriformis muscle under CT or ultrasound guidance provides both diagnostic confirmation and therapeutic benefit.
What anatomical variants of the piriformis-sciatic nerve relationship increase the risk of piriformis syndrome?
Beaton and Anson classified the relationship between the piriformis and sciatic nerve into six types. Type A (approximately 84% of individuals) has the undivided sciatic nerve exiting below an undivided piriformis — the standard anatomy. In type B, the peroneal division of the sciatic nerve passes through the piriformis while the tibial division exits below it; this affects roughly 12% of individuals and is the most common variant predisposing to piriformis syndrome. Rarer types involve the entire nerve passing through the muscle or the peroneal division above it. In these variants, contraction, spasm, or hypertrophy of the piriformis directly compresses the intramuscular sciatic nerve component. MRI with high-resolution sequences through the sciatic notch can occasionally delineate these relationships and explain why certain patients have atypical distributions of sensory loss or refractory symptoms.
What treatment options exist beyond physical therapy for refractory piriformis syndrome?
When physical therapy targeting piriformis stretching, hip rotator strengthening, and lumbopelvic stabilization fails to resolve symptoms after 6 to 8 weeks, image-guided injection of the piriformis muscle is the next intervention. Ultrasound or CT guidance is used to inject a combination of local anesthetic and corticosteroid directly into the muscle belly, with reported short-term response rates of 60–80%. Botulinum toxin type A injection is an alternative for patients with frequent recurrence, providing longer-lasting neuromuscular blockade and muscle relaxation over 3 to 4 months. For truly refractory cases with confirmed anatomical nerve entrapment — particularly in patients with a type B or rarer sciatic nerve variant demonstrated on imaging — surgical decompression via open or endoscopic piriformis release, releasing the fibromuscular constriction around the nerve, is a viable option with favorable outcomes in carefully selected patients.
Sources
- Hopayian K, Song F, Riera R, Sambandan S. The clinical features of the piriformis syndrome: a systematic review. Eur Spine J. 2010;19(12):2095-2109.
- Smoll NR. Variations of the piriformis and sciatic nerve with clinical consequence: a review. Clin Anat. 2010;23(1):8-17.
- Fishman LM, Dombi GW, Michaelsen C, et al. Piriformis syndrome: diagnosis, treatment, and outcome--a 10-year study. Arch Phys Med Rehabil. 2002;83(3):295-301.
- Fishman LM, Anderson C, Rosner B. BOTOX and physical therapy in the treatment of piriformis syndrome. Am J Phys Med Rehabil. 2002;81(12):936-942.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer